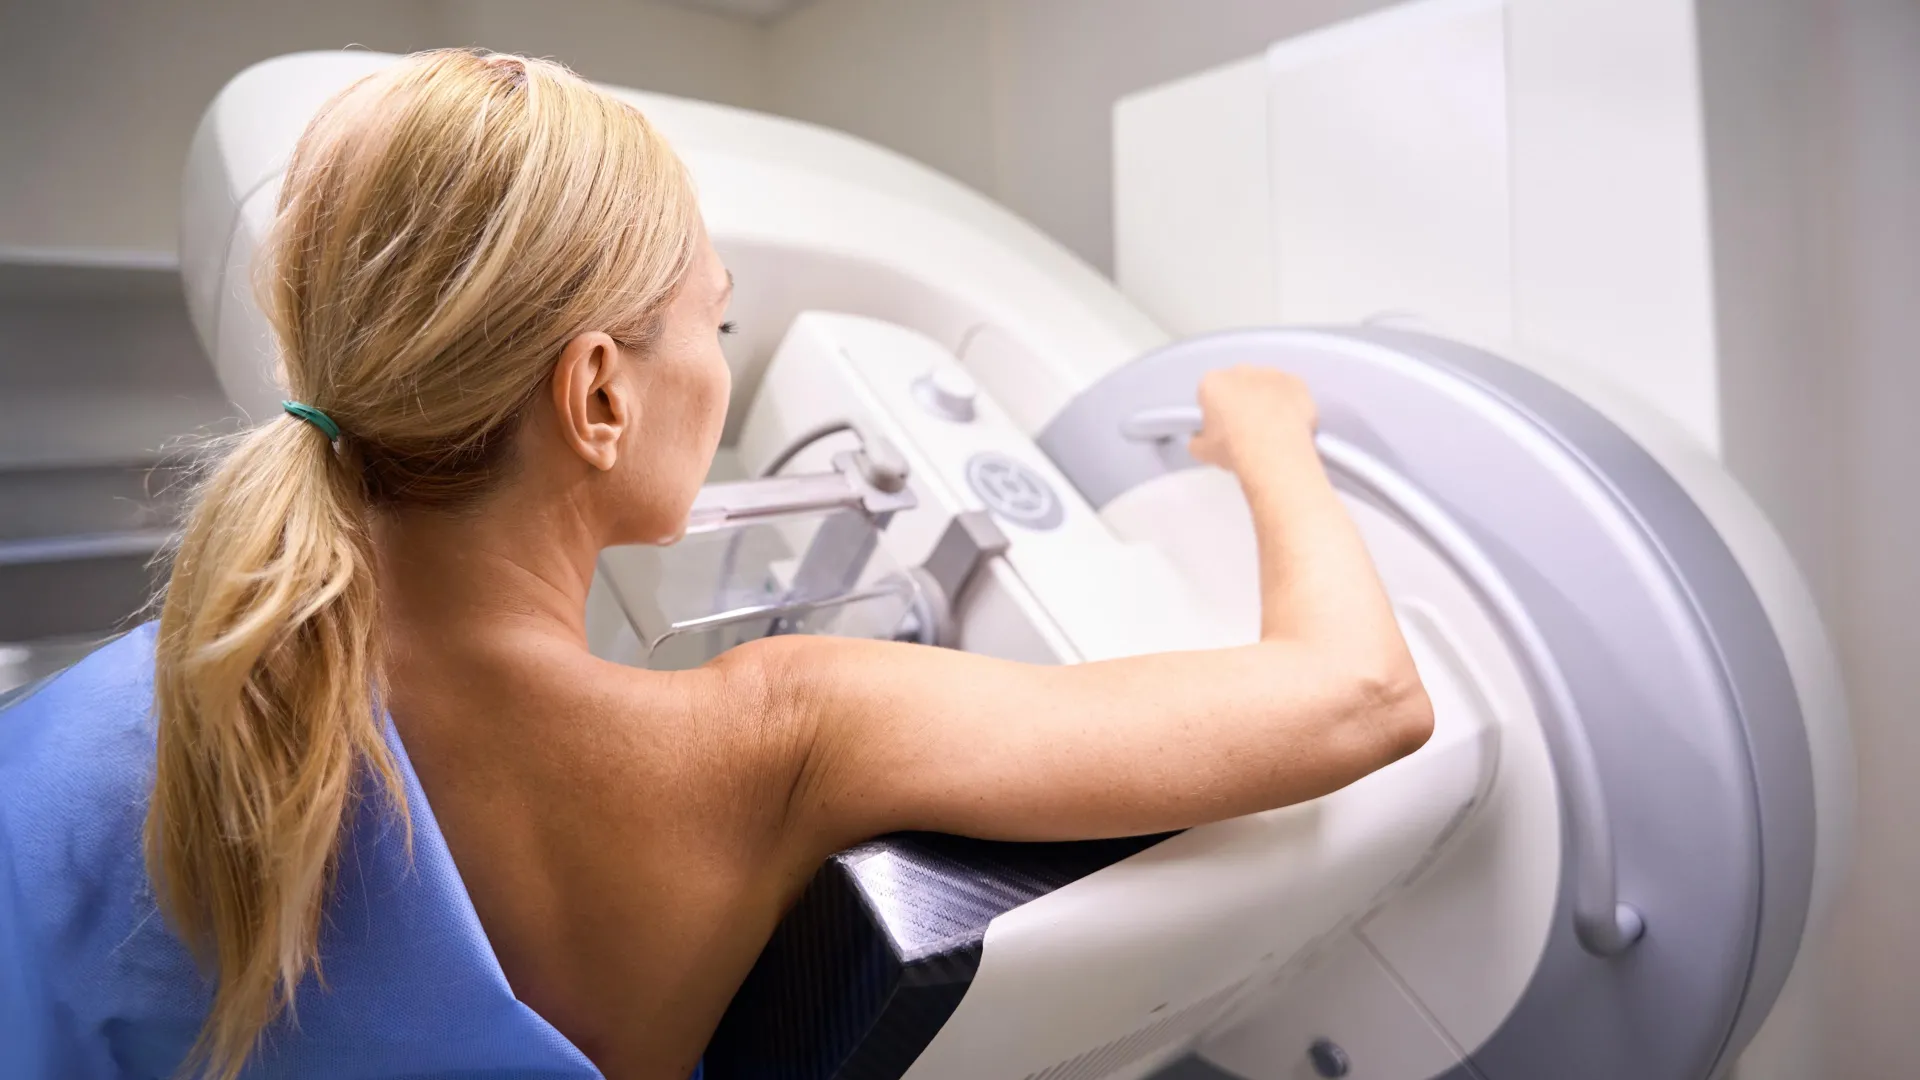
For decades, the discourse surrounding breast cancer screening has been shadowed by a persistent, unsettling statistic: the possibility that mammography identifies "cancers" that would have remained indolent or never progressed to a life-threatening stage. This phenomenon, known as overdiagnosis, has long been cited as a primary drawback of population-based screening programs, fueling intense global debate over the ethics and efficacy of routine breast cancer detection.
However, a groundbreaking study recently published by an international team of researchers suggests that the widely accepted estimates of overdiagnosis—which have reached as high as 30–50% in some academic literature—may be significantly overstated. By re-evaluating the temporal dynamics of mammography trials and comparing them against real-world data from Denmark, researchers argue that the actual rate of overdiagnosis is likely below 5%.
Main Facts: Deconstructing the Overdiagnosis Narrative
To understand the weight of this new research, one must first define what overdiagnosis entails. In the context of breast cancer, overdiagnosis occurs when screening identifies a tumor that, had it been left undetected, would never have caused symptoms or threatened a woman’s life. This can occur with slow-growing cancers that never progress, or in cases where a woman passes away from unrelated causes before a tumor would have ever become clinically apparent.
The controversy has always centered on the "cost" of early detection. If a woman is diagnosed with a cancer that would never have harmed her, she is subjected to the physical, emotional, and financial burdens of treatment—surgery, radiation, or chemotherapy—without any actual gain in life expectancy.
For years, proponents of screening and critics have clashed over the data. Critics pointed to randomized controlled trials (RCTs) from the late 20th century, which often showed a sharp spike in diagnosis rates immediately following the introduction of screening. However, this new analysis asserts that these early, high estimates failed to account for the "maturation" of trial data and the long-term patterns of incidence, leading to a profound misunderstanding of the true clinical landscape.
Chronology: The Evolution of Screening Research
The history of breast cancer screening research is long and complex, rooted in the foundational mammography trials of the 1970s and 1980s.
The Early Era of Trials
The researchers behind the new study conducted a comprehensive review of all eight major randomized trials, including the New York Health Insurance Plan (HIP) study, the Malmö trials, the Two-County study, and the Canadian National Breast Screening Study, among others. In the decades following these trials, the medical community observed that the introduction of mammography led to an immediate surge in cancer detections.
The Misinterpretation of "Incidence Spikes"
For years, the initial rise in diagnoses seen in these trials was interpreted as a sign of massive overdiagnosis. The logic seemed sound: if you look for cancer, you find more of it, therefore a portion of that "more" must be non-lethal tumors. However, this interpretation ignored the "lead-time effect"—the fact that screening catches cancers earlier than they would have appeared symptomatically.
The Danish Reference Point
The research team utilized Denmark as a unique natural experiment. Because the Danish national screening program was rolled out in different regions at different times over a span of 17 years, researchers were able to track the precise lifecycle of breast cancer diagnoses. They observed a distinct pattern: an initial rise in diagnoses followed by a long-term stabilization as the "reservoir" of screen-detected cancers was exhausted. By applying this "temporal context" to the historical randomized trials, the researchers discovered that the data from those trials actually mirror the much lower overdiagnosis rates observed in modern, organized, and stable screening environments.
Supporting Data: Why Timing and Context Matter
The core of the study, led by Sisse Helle Njor of the University of Southern Denmark and Lillebælt Hospital, lies in the realization that data interpretation is highly sensitive to time.
The Lead-Time Effect
When a screening program begins, there is an artificial "bubble" of diagnosis. Cancers that would have been found in years three, four, or five are found in year one. If a study stops prematurely—before the expected "lull" in future diagnoses occurs—researchers are left with a statistical anomaly that looks like overdiagnosis but is actually just a shift in the timeline of detection.
The Contamination Factor
Another flaw in earlier estimates was "contamination." In many randomized trials, women in the control group (who were not supposed to be screened) eventually sought mammography outside the study parameters. This blurred the lines between the groups, further complicating the statistical output.
Comparative Analysis
By comparing the incidence of both invasive breast cancer and ductal carcinoma in situ (DCIS) at matching points in time, the researchers found that the patterns in the original trials were not outliers. Instead, they were consistent with a biological reality where overdiagnosis is a minor, rather than a systemic, problem.
"When interpreted in their full temporal context," explains Matejka Rebolj, Senior Epidemiologist at Queen Mary University of London, "randomized trial data are consistent with overdiagnosis of less than five percent, rather than with estimates nearing 50%."
Official Responses: Shifting the Paradigm
The professional community is already reacting to the study as a potential "paradigm shift" in how public health officials communicate with women.
Professor Sisse Helle Njor emphasizes that the primary goal of this research is to provide a "more realistic interpretation of the evidence." For years, the fear of overdiagnosis has been a central component of the "decision aids" provided to women when they are invited for screening. If women believe there is a 50% chance that their diagnosis is "unnecessary," they may opt out of a life-saving procedure.
"Most women will not develop breast cancer," says Njor, "but with this study, we can now be reassured that the benefits of detecting breast cancer early and preventing premature death will outweigh the small risk of unnecessary treatment."
The study has been lauded for its rigorous methodology, particularly its focus on the "temporal context" of data. By stripping away the statistical noise created by short-term trial horizons, the researchers have managed to reconcile decades of conflicting literature.
Implications: The Future of Screening Communication
The implications of these findings extend far beyond academic journals. They strike at the heart of public health policy and individual patient autonomy.
Reforming Patient Information
Currently, many screening brochures emphasize the potential harms of overdiagnosis to ensure "informed consent." If those brochures are based on outdated, inflated figures, they may be doing a disservice to the public. Health authorities may now look to revise these materials to reflect that while overdiagnosis exists, it is a relatively rare event.
Reassuring the Public
For the millions of women worldwide who participate in screening, the news is largely positive. The "harm" of overdiagnosis has long been the primary psychological barrier to screening participation. By reframing the risk as marginal, health advocates hope to increase screening compliance, which remains the single most effective tool for reducing breast cancer mortality.
A Framework for Future Studies
The study also provides a blueprint for how to analyze future screening data. The researchers have demonstrated that one cannot look at a snapshot of data; one must look at the "movie"—the full timeline of incidence and mortality—to understand the impact of any screening program.
A Note on Funding and Integrity
The research was supported by the Novo Nordisk Foundation and Cancer Research UK, ensuring the independence and depth of the analysis. By meticulously examining the eight primary randomized trials that have served as the bedrock of screening science, the team has not only provided a new answer to an old question but has also demonstrated the value of revisiting foundational research with modern statistical tools.
Conclusion
As we look toward the future of oncology and public health, the message from this study is clear: context is everything. By correcting the misinterpretations of the past, researchers have cleared the way for a more accurate, less fearful, and more evidence-based approach to breast cancer screening. For women, this means more confidence in the screening process, and for the medical community, it means a more precise understanding of the balance between the benefits of early detection and the risks of medical intervention. The "overdiagnosis crisis," it seems, was largely a crisis of interpretation.